
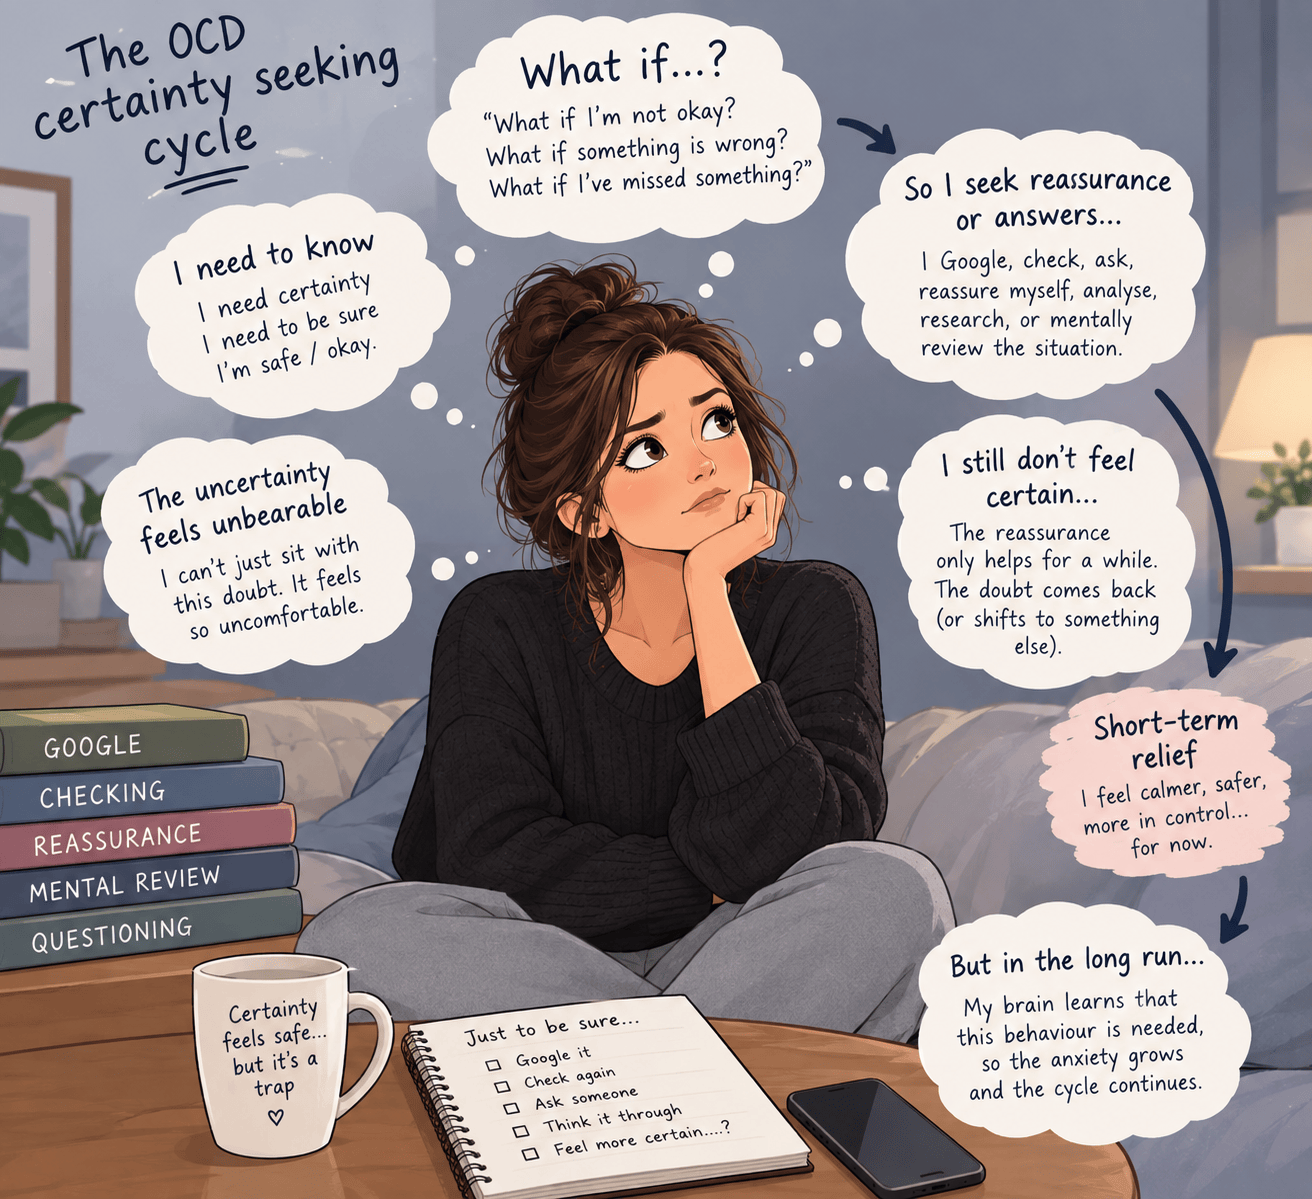
There is something slightly ironic about OCD. The things we do to try to make ourselves feel better can sometimes be the very things that keep OCD going. This is a concept I cover a lot when working with OCD: sometimes the solution becomes the problem. When we’re anxious, it makes complete sense that we want to make it better. Anxiety is uncomfortable, and when that anxiety is being driven by an intrusive thought or a nagging sense that something isn’t quite right, our instinct is often to try to work out what is going on. We want an explanation, reassurance, certainty or some way of knowing that we’re okay. If we can find that answer, we feel better. The difficulty is that our brain then learns that we needed to do something to get rid of the anxiety.
This is an important part of understanding why compulsions can become so persistent. Checking the door can make you feel more certain that it’s locked. Asking your partner whether they think you’re a good person can make you feel reassured. Googling an intrusive thought can produce an explanation that makes the thought feel less frightening. None of these things are inherently ridiculous or irrational responses to uncertainty. In fact, they make perfect sense if your goal is to feel certain and safe. The problem is that OCD doesn’t tend to stop at “That’s enough.” The relief is short-term, the doubt returns, and your brain has now learned that the way to deal with that doubt is to check again, ask again, research again or think about it a little more.
I think this can be particularly difficult for some people with OCD because, in my experience, many of the people I work with are incredibly thoughtful, imaginative, creative and conscitentious. They can see possibilities that other people might not consider, make connections quickly and create incredibly detailed stories in their minds. The problem is that a creative mind doesn’t only have the capacity to imagine good stories; it can imagine frightening ones too. Give it a “What if?” and it can build an entire narrative around it. One possibility leads to another, and suddenly something that started as a fleeting thought has become a complicated scenario that feels as though it needs to be examined.
I also see a lot of people with OCD who are natural problem-solvers. They are people who have spent much of their lives being good at figuring things out. When something is difficult, they think about it, analyse it from different angles, gather information and work out what to do next. That is a hugely useful skill in many areas of life, for example, if you’re faced with a difficult problem at work, thinking it through can help you find a solution. If you’ve made a mistake, reflecting on what happened can help you avoid making the same mistake again. The difficulty is that OCD presents uncertainty as though it were a problem that can be solved through thinking. For someone who has learned throughout their life that thinking carefully and finding the right answer is how you deal with difficult things, OCD’s invitation to “just think about it a little more” can be incredibly persuasive.
It often sounds like, “I just need to work out what this thought means,” or “I need to remember exactly what happened,” or “If I can understand why I had that thought, I’ll know whether I need to be worried.” The person isn’t necessarily consciously trying to avoid their anxiety. They may genuinely believe they’re dealing with it. They’re trying to solve the problem in the same way they’ve solved other difficult problems throughout their life. The catch is that some of the questions OCD asks simply don’t have the kind of definitive answer that our problem-solving mind is looking for.
This is one reason why trying to understand OCD itself can sometimes become part of OCD. Learning about OCD is generally a very good thing -understanding intrusive thoughts, compulsions and avoidance can help people recognise what is happening and make sense of experiences that may have previously felt frightening or incomprehensible. But there can be a subtle shift from learning about OCD to checking about OCD. You might start by reading an article about intrusive thoughts, then find another article that describes your experience even more closely. You read about different OCD subtypes and start wondering which one you have. You take an online questionnaire, then another because you’re not sure whether you answered the first one correctly. You search forums to see whether other people have had exactly the same thought. You find someone who has had a remarkably similar experience and feel reassured, but then notice one small difference and start wondering what that difference means.
At that point, you’re potentially no longer learning something new. You’re trying to reach a feeling of certainty. And OCD is very good at moving the goalposts. You find an answer to one question and another question appears. You reassure yourself that having a thought doesn’t mean you want to act on it, but then your mind asks whether you can be completely certain about that. You read that intrusive thoughts don’t reflect your character, but then start analysing whether your particular thought was too vivid, too specific or felt too real for that reassurance to apply. The information you’ve found might be completely accurate, but the problem is the function it’s serving. Are you reading because you’re interested in understanding OCD, or because you need the information to make the anxiety go away?
The same thing happens with reassurance. Imagine someone has the thought, “What if I’m actually a bad person?” They ask their partner, “Do you think I’m a good person?” Their partner says yes, of course they do, and the anxiety settles. For a while, everything feels okay. Then the doubt returns, perhaps in a slightly different form: “But you really don’t think I’m a bad person, do you?” The partner reassures them again. It can be very difficult to understand why that answer doesn’t eventually become enough, but OCD isn’t really looking for an answer; it’s looking for certainty, and certainty is something none of us can achieve completely.
Memory is a particularly good example of how this can backfire. Someone might remember locking the front door but then have the thought, “Did I actually lock it?” They go back and check and see that it is locked, so they feel reassured. But later another doubt appears: “Did I check the right door?” So they check again. Then perhaps they wonder whether they were actually paying attention when they checked, or whether they’re remembering the first check or the second check. The more they check, the more complicated the memory becomes. Repeated checking can actually undermine confidence in memory rather than strengthen it. We’re adding more and more moments that now need to be remembered and distinguished from one another. Instead of reducing doubt, we’re multiplying opportunities for doubt: Was that definitely what I saw? Was I paying attention? Did I really remember doing it, or am I remembering checking it? This is why someone with OCD can genuinely feel as though their memory is becoming unreliable. It isn’t necessarily that their memory was poor in the first place. Their repeated attempts to achieve absolute certainty may simply be creating more uncertainty.
There is a useful parallel here with the way people can sometimes use alcohol or drugs to manage anxiety. Someone who feels socially anxious might have a drink before going to a party and discover that the alcohol makes them feel more relaxed and less self-conscious. Their brain has learned that alcohol provides relief from anxiety. Over time, they may become increasingly reluctant to face social situations without it, because the thing they discovered as a solution to the anxiety has become something they feel they need in order to cope with the anxiety. Not only that but they rely on ever increasing amounts of alcohol to achieve the same result- it just isn’t enough anymore. Like in OCD, the behaviour is being reinforced because it removes something unpleasant in the short term. Only in OCD, that behaviour might be checking, reassurance seeking, rumination, avoidance or researching rather than drinking, but the important learning can be similar: “When I feel this uncomfortable, I need to do something to make the feeling go away.”
This is also why I think it’s important not to simply tell someone with OCD to stop researching or stop asking for reassurance. These behaviours usually make sense to the person doing them. They have a purpose. They are an attempt to cope with something that feels genuinely distressing. The more useful question is what the behaviour is doing for them. If you’re reading about OCD because you want to understand what ERP means, that’s very different from spending another two hours searching because you need to know whether your particular thought definitely counts as OCD. If you’re asking your therapist a question because you need information to help with treatment, that’s different from asking the same question in several different ways because you haven’t quite achieved the feeling of certainty you’re looking for.
And this is where AI creates a particularly interesting new version of the same problem. It is now incredibly easy to describe an intrusive thought or an uncomfortable situation to an AI tool and ask it to explain what it means. You can ask whether your thought is normal, whether your reaction means something about you, whether what happened sounds like OCD, whether you’ve done something wrong or whether you’re doing ERP correctly. You can then ask a follow-up question, and another one, and another one, until the answer feels reassuring enough. The technology itself isn’t necessarily the problem; AI can be a useful source of general information. But if you find yourself repeatedly returning to it whenever doubt appears because you need another answer before you can move on, it may be functioning as reassurance in exactly the same way that Google, Reddit, a partner or even a therapist can.
So what do we do instead? The answer can feel frustratingly simple: we practise not solving the uncertainty. That doesn’t mean ignoring genuine problems or refusing to seek appropriate information. It means becoming more comfortable with the fact that OCD will sometimes present you with a question that cannot be answered with complete certainty. You might notice the urge to Google something and decide not to. You might want to ask your partner for reassurance but allow the question to remain unanswered. You might notice yourself mentally replaying something that happened earlier in the day and decide not to keep analysing it. At first, this can feel worse, because you’ve removed the thing you normally use to bring the anxiety down. But that discomfort is part of the learning. You’re giving your brain the opportunity to discover that uncertainty can be uncomfortable without being dangerous, and that you don’t have to resolve it before you can carry on with your life.
Ultimately, you don’t need to understand your OCD perfectly in order to recover from it. You don’t need to identify every subtype, find an explanation for every intrusive thought, remember every detail of every situation or become completely certain that you’re doing ERP correctly. In fact, seeking that certainty can sometimes become the very thing keeping you stuck. Recovery is about becoming increasingly willing to have unanswered questions and still get on with the things that matter to you (your values).
So if you find yourself spending hours reading about OCD, asking questions, checking your memory, seeking reassurance or trying to understand your thoughts from every possible angle, it can be useful to pause before looking for the next answer and ask yourself one simple question: “Am I learning something useful, or am I trying to make uncertainty go away?” Sometimes the thing we’re using to solve the problem has quietly become part of the problem itself. And when that happens, the answer isn’t necessarily to find a better solution. Sometimes the solution is learning that you don’t need one.

